Can Pitocin Cause a Birth Injury? Tachysystole Explained
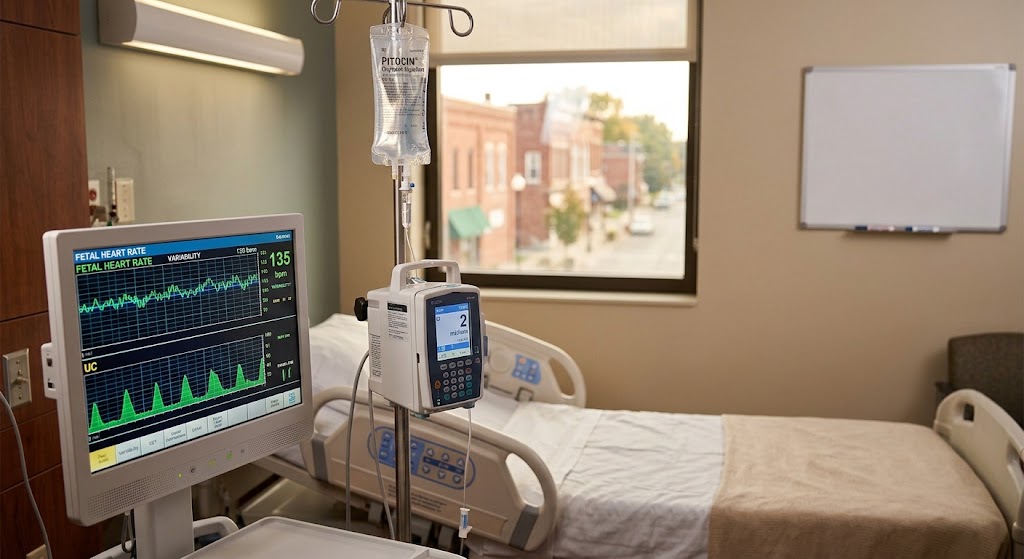
Many labors in Indiana begin or speed up with a small bag of clear fluid hung beside the bed. The nurse calls it Pitocin, explains that it will help the contractions come along, and adjusts the pump every so often. For most families that is the last time they think about it. But if your baby was born in distress after an induced or augmented labor, you may have found yourself replaying the hours before delivery and asking, “Were the contractions coming too fast?” or “Did anyone turn that medication down when the baby’s heart rate dropped?”
Those are reasonable questions. Pitocin is one of the most commonly used drugs on a labor and delivery unit, and when it is monitored and adjusted properly, it is generally safe for both mother and baby. The concern arises when the drug pushes the uterus into a pattern of contractions that are too frequent or too long, a condition clinicians call uterine tachysystole (sometimes still referred to as hyperstimulation). This article explains what Pitocin does, why tachysystole matters to a baby’s oxygen supply, what the standard of care generally expects from the care team, and what it may mean if you believe those expectations were not met.
Key Takeaways for Parents
- Pitocin is a high-alert medication. Because it is the synthetic form of oxytocin, the body’s own labor hormone, its effects are dose-related and can change quickly. Hospital protocols generally require a nurse to be continuously monitoring the mother’s contractions and the baby’s heart rate whenever it is running.
- Tachysystole has a specific clinical definition. ACOG defines it as more than five contractions in 10 minutes, averaged over a 30-minute window. Contractions that last two minutes or longer, or that leave less than a minute of rest between them, are also generally treated as excessive uterine activity.
- The baby needs the rest between contractions. Each contraction briefly reduces blood flow through the placenta. When contractions come too close together, the baby’s oxygen reserve can fall, which is why tachysystole is a recognized contributor to fetal distress and, in some cases, hypoxic-ischemic encephalopathy (HIE).
- The standard response is to reduce or stop the drug. ACOG guidance and most hospital protocols call for decreasing or discontinuing oxytocin when tachysystole occurs, particularly if the fetal heart rate tracing is Category II or III. Continuing to increase the dose through a worsening tracing is a common focus of medical record reviews.
- Indiana has its own claim process. Birth injury claims in Indiana generally must be filed within two years, though a child injured before age six generally has until their eighth birthday, and most claims must first go through a Medical Review Panel before reaching a courtroom.
What Is Pitocin, and Why Is It Used?
Pitocin is the brand name for synthetic oxytocin, a copy of the hormone the body releases naturally to make the uterus contract. It is given through an IV pump, measured in milliunits per minute, and adjusted (“titrated”) up or down by the labor nurse under standing orders from the obstetrician. Because the drug is cleared from the bloodstream within minutes (published estimates range from roughly 3 to 12 minutes), its effects on contractions generally ease fairly quickly once the infusion is slowed or stopped, which is one reason careful titration matters so much. It also takes about 40 minutes for the drug to reach a steady level in the blood after each dose change, which is why protocols space increases apart.
Oxytocin is used in two broad situations. The first is induction of labor, which means starting labor before it begins on its own, generally because continuing the pregnancy carries more risk than delivery. Common reasons include a pregnancy past 41 weeks, preeclampsia or other maternal conditions, ruptured membranes without labor, or concerns about the baby’s growth. The second is augmentation of labor, which means strengthening or speeding up contractions in a labor that has already started but has slowed or stalled.
ACOG’s induction of labor guidance describes both low-dose and high-dose oxytocin protocols. Hospitals generally adopt one and write it into a standing order set that tells nurses the starting rate, how much to increase it, how often, and when to stop. The Institute for Safe Medication Practices lists IV oxytocin among its high-alert medications, a designation for drugs that carry an elevated risk of serious harm when used in error. In practice, that designation is why most labor units require continuous electronic fetal monitoring whenever the drug is running, and why the medication record is expected to show a documented assessment before each dose increase.
Low-Dose and High-Dose Protocols
Hospitals generally follow one of two approaches, and it helps to know which one your hospital uses because it changes what “normal” looks like in the records.
Low-dose protocols typically start at 0.5 to 2 milliunits per minute and increase by 1 to 2 milliunits every 15 to 40 minutes. The slower pace gives the uterus time to respond to each change before the next one, which is why these protocols are associated with less tachysystole. High-dose protocols typically start at around 6 milliunits per minute and increase by 3 to 6 milliunits every 15 to 40 minutes. They tend to shorten labor slightly but carry a higher rate of tachysystole, and they generally require closer monitoring.
What Is Uterine Tachysystole?
Tachysystole is the clinical term for contractions that come too often. ACOG defines it as more than five contractions in a 10-minute period, averaged over a 30-minute window. Many hospital protocols and nursing references also treat other patterns as excessive uterine activity even when the five-in-ten count is not reached: a single contraction lasting two minutes or longer, contractions of normal length that occur within one minute of each other, or a uterus that does not fully relax between contractions (what clinicians call elevated resting tone).
The word “hyperstimulation” was once used interchangeably, but current ACOG terminology reserves “tachysystole” for the pattern itself and asks clinicians to note separately whether the fetal heart rate is showing changes alongside it. Tachysystole can occur in spontaneous labor, but it is considerably more common when oxytocin or a cervical ripening agent such as misoprostol is in use, and the risk generally rises with the dose.
Why Frequent Contractions Matter to the Baby
During a contraction, the muscle of the uterus squeezes the blood vessels that carry oxygenated blood to the placenta. This is normal and expected; a healthy baby has enough reserve to tolerate it. The rest period between contractions is when blood flow returns and the baby’s oxygen level recovers. When that rest period shrinks, the baby has less time to recover before the next contraction begins. Research on fetal oxygenation has shown that oxygen levels in the baby’s blood decline measurably over a stretch of tachysystole, and clinicians are generally taught that the effect builds over minutes rather than seconds.
The first sign of that strain usually appears on the fetal heart rate monitor. The tracing may show recurrent late decelerations (dips that begin after the peak of a contraction), a loss of the normal moment-to-moment variability, or, in more serious cases, the patterns that define a Category III tracing. If the pattern is not corrected, prolonged oxygen deprivation can lead to the kind of brain injury discussed in the firm’s articles on HIE and cerebral palsy.
Excessive uterine activity also places stress on the uterus itself. In a mother who has had a prior cesarean or other uterine surgery, prolonged tachysystole is a recognized risk factor for uterine rupture, which is an emergency for both mother and baby.
Reading the Fetal Monitor in Plain Language
Almost every question about Pitocin management comes back to the fetal heart rate monitor, so it helps to understand what the two lines on that strip mean.
The top line is the baby’s heart rate. A healthy baby at term generally has a baseline between 110 and 160 beats per minute, with small, constant fluctuations. Those fluctuations are called variability, and clinicians treat them as one of the most reassuring signs available, because they indicate that the baby’s nervous system is well-oxygenated and responding normally.
The bottom line is the contractions. Each hump shows a contraction building, peaking, and easing. The space between humps is the rest period. The monitor may also show a number for the uterine resting tone, which should return to a low baseline between contractions.
Decelerations are temporary dips in the baby’s heart rate. Their timing relative to the contraction is what matters. Early decelerations mirror the contraction, dipping and recovering at the same time; they are generally caused by pressure on the baby’s head and are considered normal. Variable decelerations are abrupt, V-shaped dips that may occur at any point and usually reflect the umbilical cord being compressed. Occasional ones are common, while frequent or deep ones are watched closely. Late decelerations begin after the contraction peaks and recover after it ends. They generally indicate that the placenta is not delivering enough oxygen during the contraction, and recurrent late decelerations are one of the classic signatures of tachysystole.
The three categories. ACOG groups tracings into Category I (normal), Category II (indeterminate, requiring evaluation and continued surveillance), and Category III (abnormal, requiring prompt intervention). Category III includes absent variability combined with recurrent late decelerations, recurrent variable decelerations, or a slow baseline (bradycardia), as well as a sinusoidal pattern. The category matters for oxytocin because ACOG’s management guidance ties the response to it: reduce the dose for tachysystole with Category I, stop the drug for tachysystole with Category II or III.
How Tachysystole Differs From a Strong, Normal Labor
Parents sometimes hear that their labor was “intense” or “fast” and wonder whether that was tachysystole. Strong contractions are not the problem; frequent contractions without adequate rest are. A labor with contractions every three minutes, each lasting a minute, is well within normal. A labor with contractions every 90 seconds, or with contractions that run into each other so that the uterus never fully relaxes, is not. The distinction is one a nurse can generally see on the monitor and feel by hand on the mother’s abdomen, which is why the nursing notes should record both the frequency and the resting tone.
What the Standard of Care Generally Expects
There is no single national rule that fixes the maximum oxytocin dose or the exact moment the drug must be stopped. What exists is a combination of ACOG guidance, nursing practice standards from AWHONN (the Association of Women’s Health, Obstetric and Neonatal Nurses), and the hospital’s own written protocol. Taken together, they generally describe the following expectations.
Continuous monitoring. Whenever oxytocin is infusing, the mother’s contractions and the baby’s heart rate are generally expected to be monitored continuously, with the nurse documenting the pattern at regular intervals (often every 15 to 30 minutes in the first stage of labor and more frequently in the second).
Assessment before every increase. The dose is generally not supposed to rise on a fixed schedule alone. Before each increase, the nurse is expected to confirm that the contraction pattern is not already adequate, that the fetal heart rate is reassuring, and that the uterus is relaxing between contractions. Once contractions are adequate (commonly three to five in 10 minutes, each lasting roughly 60 to 90 seconds), most protocols call for holding the dose rather than continuing to increase it.
Responding to tachysystole. ACOG’s guidance on managing intrapartum fetal heart rate tracings lays out a stepwise response. When tachysystole appears with a Category I (normal) tracing, the dose is generally reduced. When it appears with a Category II or III tracing, the oxytocin is generally stopped altogether, and the team turns to the standard intrauterine resuscitation measures: repositioning the mother, giving IV fluids, checking blood pressure, and administering oxygen when appropriate. If the pattern persists after the drug is paused, ACOG suggests a rapid-acting uterine relaxant such as terbutaline.
Escalation and communication. If the tracing does not recover, the nurse is expected to notify the physician or midwife promptly, and the provider is expected to evaluate the patient in person and decide whether to proceed toward cesarean delivery. Hospital chain-of-command policies exist precisely so that a nurse who disagrees with a provider’s decision to continue can escalate the concern.
Restarting carefully. When oxytocin has been stopped for tachysystole and the tracing has recovered, protocols generally allow it to be restarted at a lower rate, often half the rate that caused the problem, rather than at the previous dose.
Intrauterine Resuscitation, Step by Step
“Intrauterine resuscitation” sounds dramatic, but it describes a short list of bedside measures aimed at getting more oxygen to the baby while the team decides what to do next. When tachysystole is accompanied by a concerning tracing, the sequence generally looks like this:
- Stop or reduce the oxytocin. This is the single most important step, because it addresses the cause rather than the symptom.
- Reposition the mother. Turning her onto her left side (or the opposite side from the current position) takes pressure off the large vessels that supply the uterus.
- Give an IV fluid bolus. Extra fluid raises blood pressure and improves blood flow to the placenta, particularly if an epidural has lowered the mother’s pressure.
- Check maternal blood pressure and treat it if low. Epidural-related hypotension is a common, correctable contributor.
- Consider oxygen. Practice has shifted here. ACOG’s 2025 guidance recommends against routine maternal oxygen for Category II or III tracings unless the mother’s own oxygen level is low, so the absence of oxygen from the record is generally not a concern by itself.
- Consider a uterine relaxant. If tachysystole persists after the drug is stopped, ACOG suggests a rapid-acting agent such as terbutaline, which relaxes the uterus within minutes.
- Notify the provider and prepare for delivery. If the tracing does not improve, the team is expected to move toward delivery, whether by an expedited vaginal birth or a cesarean.
Each of these steps should appear in the nursing notes with a time. A record that shows tachysystole charted at 2:10 a.m. and the first intervention charted at 2:55 a.m. raises a question that an expert will want answered.
None of these steps guarantee a good outcome, and tachysystole can occur even when every step is followed. The standard of care is about the response, not the mere occurrence.
Birth Injuries Associated With Oxytocin Misuse
When tachysystole goes unrecognized or is allowed to continue through a worsening fetal heart rate tracing, the injuries that follow are generally the injuries of oxygen deprivation and, less often, of physical trauma to the uterus. They may include:
- Hypoxic-ischemic encephalopathy (HIE): Brain injury from inadequate oxygen and blood flow, which may be treated with therapeutic cooling in the hours after birth.
- Cerebral palsy: A group of lifelong movement disorders that can result from brain injury around the time of birth.
- Neonatal seizures and developmental delays: Sometimes the earliest visible signs of an underlying hypoxic injury.
- Meconium aspiration: A baby under stress may pass stool in the womb and inhale it, causing breathing difficulty after birth.
- Low Apgar scores and NICU admission: Not injuries in themselves, but often the first documented indication that something went wrong.
- Uterine rupture and placental abruption: Maternal emergencies that can also cut off the baby’s oxygen supply abruptly.
- Postpartum hemorrhage: A uterus that has been overstimulated for hours may not contract effectively after delivery.
It bears repeating that many babies exposed to tachysystole are born healthy, and that HIE and cerebral palsy have causes unrelated to labor management. Whether a particular injury can be tied to oxytocin management is a medical question that generally requires review of the complete fetal monitoring strip alongside the medication record.
How an Oxygen-Related Injury Is Identified After Birth
Parents often learn that something went wrong in pieces: a low Apgar score mentioned in passing, a transfer to the NICU, a conversation about “cooling” the baby. Understanding what these steps mean can help families make sense of the records later.
Apgar scores. The Apgar is a quick 0-to-10 assessment of the baby’s color, heart rate, reflexes, muscle tone, and breathing at one and five minutes after birth. A five-minute score of 7 or above is generally considered reassuring. A score below 7 at five minutes, particularly one that remains low at 10 minutes, is a signal that the baby had a difficult transition and generally triggers further evaluation.
Umbilical cord blood gases. When a baby is born in distress, the team generally draws blood from the umbilical cord to measure its acidity (pH) and “base deficit.” These numbers reflect how much oxygen the baby was getting in the period just before birth. A cord arterial pH below 7.0 and a base deficit of 12 or more are generally treated as evidence of significant oxygen deprivation around the time of delivery. These values are among the most important pieces of objective evidence in a birth injury case because they are measured, not interpreted.
Therapeutic hypothermia (“cooling”). For babies born at 36 weeks or later (some centers treat babies as early as 35 weeks) who meet criteria for moderate or severe HIE, standard treatment is to lower the baby’s body temperature to about 33.5 degrees Celsius for 72 hours, beginning within six hours of birth. Cooling can reduce the extent of brain injury but does not reverse it, which is why the timing matters. If your baby was cooled, the hospital has already documented that it believed a significant hypoxic event occurred.
None of these findings alone establishes that oxytocin was mismanaged. What they do is establish that a hypoxic injury occurred and roughly when, which is the foundation on which the review of the labor records is built.
What Families Can Look For in the Medical Records
The question of whether oxytocin was managed appropriately is generally answered by three documents read side by side: the electronic fetal monitoring strip, the medication administration record (MAR) or infusion pump log, and the nursing flowsheet. Parents have the right to request all three from the hospital’s medical records department, along with the physician’s progress notes and the delivery summary.
When reviewing those records, a medical expert will generally be looking for patterns such as:
- Dose increases without a documented assessment. The MAR shows the rate going up every 20 or 30 minutes, but the nursing notes do not record contraction frequency, resting tone, or fetal heart rate before each change.
- Continued increases after contractions were already adequate. The flowsheet documents contractions every two minutes, yet the dose kept climbing.
- Tachysystole charted without a response. The nurse notes six or more contractions in 10 minutes, but the pump rate stays the same or increases, and there is no record of repositioning, fluids, or provider notification.
- A gap between a non-reassuring tracing and the physician’s arrival. Late decelerations begin at one time; the provider’s note is timed 45 minutes later.
- The drug restarted at the same rate that caused the problem. After a pause, the infusion resumes at full dose rather than at a reduced rate.
- Missing or incomplete strips. The fetal monitoring record is missing a segment, was printed only in summary form, or ends before delivery.
Parents are not expected to interpret a fetal heart rate strip on their own. What matters at this stage is preserving the complete record, including the electronic monitoring data, before it is archived or purged under the hospital’s retention schedule.
Is an Oxytocin-Related Injury Medical Malpractice?
Not automatically. Tachysystole is a known, sometimes unavoidable side effect of a drug that is used in a large share of U.S. deliveries. A birth injury claim in Indiana generally requires proof of four elements: that a provider-patient relationship existed, that the provider breached the accepted standard of care, that the breach caused the injury, and that the injury resulted in damages. In the oxytocin context, the breach usually centers on the response to tachysystole or to a deteriorating fetal heart rate tracing, not on the decision to use the drug in the first place.
Because labor nurses administer and titrate the drug under the physician’s orders, these claims may involve the hospital (as the nurses’ employer), the attending obstetrician or midwife, or both. Hospital protocols, unit staffing records, and the chain-of-command policy in effect at the time can all become relevant. An experienced birth injury attorney will generally retain obstetric and nursing experts to review the strip and the MAR together and offer an opinion on whether the care met the standard and whether the timing of events supports a causal link to the child’s diagnosis.
Indiana’s Birth Injury Claim Process
Birth injury claims in Indiana fall under the Indiana Medical Malpractice Act, which shapes both the timeline and the procedure.
Time limits. Under Indiana Code § 34-18-7-1, a medical malpractice claim generally must be filed within two years of the alleged malpractice. For a child who was under six years old when the injury occurred, the statute generally extends that deadline to the child’s eighth birthday. Because oxytocin-related injuries often surface as developmental concerns months or years after birth, this extension can be significant, but families should not assume they have the full window, since related claims (such as a parent’s own claim) may be subject to the shorter period.
The Medical Review Panel. Before most claims can proceed to trial, the proposed complaint generally must be submitted to a Medical Review Panel administered through the Indiana Department of Insurance. The panel, made up of three health care providers and an attorney chairperson, reviews the records and expert submissions and issues an opinion on whether the standard of care was met. The opinion is admissible but not binding.
Damages. Indiana caps the total recovery in a medical malpractice case. For malpractice occurring after June 30, 2019, the cap is $1.8 million per injury under Indiana Code § 34-18-14-3. The health care provider is responsible for the first $500,000, and the state’s Patient’s Compensation Fund is responsible for amounts above that, up to the cap. Earlier dates of injury are subject to lower caps, so the figure that applies depends on the date of the child’s birth.
What You Can Do Next
Understanding what happened during an induced or augmented labor starts with the monitoring strip and the medication record, not with guesswork about what the nurse said or how the room felt. A qualified birth injury attorney, working with independent obstetric and nursing experts, can review those records to evaluate whether the response to tachysystole and to the fetal heart rate tracing met the standard of care.
If you have questions about oxytocin, tachysystole, or a birth injury in Indiana, Powless Law can help you secure your complete labor and delivery records and obtain a clear evaluation of your situation. Contacting us or sending an inquiry does not establish an attorney-client relationship until a formal representation agreement is signed.
Disclaimer: This article is for general informational and educational purposes only and does not constitute formal medical or legal advice. Every birth record is unique, and reading this material or contacting Powless Law does not create an attorney-client relationship. Past medical or legal outcomes discussed do not guarantee future results.
Frequently Asked Questions
Can Pitocin cause brain damage in a baby?
Not directly. Pitocin does not harm the baby’s brain by itself. The risk arises when it causes contractions that are too frequent or too long, reducing the oxygen reaching the baby over an extended period. When that pattern is not corrected, the resulting oxygen deprivation can lead to injuries such as HIE. Properly monitored and titrated oxytocin is generally considered safe.
What is a normal contraction pattern on Pitocin?
Most protocols aim for three to five contractions in a 10-minute period, each lasting roughly 60 to 90 seconds, with the uterus fully relaxing in between. More than five in 10 minutes, averaged over 30 minutes, meets ACOG’s definition of tachysystole.
Should the nurse have turned the Pitocin off when my baby’s heart rate dropped?
It depends on what the tracing showed. ACOG guidance generally calls for reducing the dose when tachysystole occurs with a normal (Category I) tracing and stopping it when the tracing is Category II or III. Whether the response in your case was appropriate generally requires a review of the full strip and the medication record by an obstetric expert.
How do I find out how much Pitocin I received?
The medication administration record and the IV pump log will show the rate in milliunits per minute and the time of each change. You can request these along with the fetal monitoring strip from the hospital’s medical records or health information management department. Ask specifically for the complete electronic fetal monitoring data, not just a summary.
How long do I have to file a birth injury claim in Indiana?
Generally two years from the date of the alleged malpractice. If the child was under six at the time, the deadline generally extends to the child’s eighth birthday. Most claims must first be submitted to a Medical Review Panel.
Is tachysystole the same thing as hyperstimulation?
Essentially, yes. “Hyperstimulation” was the older term, and some clinicians still use it. Since a 2008 National Institutes of Health workshop, whose terminology ACOG adopted the following year, the recommended term has been “tachysystole” to describe the contraction pattern itself, with a separate note about whether the fetal heart rate was affected. If you see either word in your records, it is worth asking what the fetal heart rate showed at the same time.
My baby was cooled after birth. Does that mean something went wrong during labor?
Cooling means the medical team determined that your baby met the criteria for moderate or severe HIE, which generally means a significant oxygen-related event occurred around the time of birth. It does not, by itself, mean that anyone was negligent. HIE can have causes unrelated to labor management. It does mean that the labor records deserve a careful review.
What if the hospital says the fetal monitoring strip is no longer available?
Indiana law (Indiana Code § 16-39-7-1) generally requires health care providers to keep original health records for at least seven years, and electronic fetal monitoring data is part of the medical record. If a hospital reports that the strip cannot be located, an attorney can generally send a formal preservation request and, if necessary, pursue the issue through the claim process. Missing records are taken seriously, and the loss of a strip can itself become an issue in the case.
At the Powless Law Firm, we dedicate our practice to helping families navigate the aftermath of medical malpractice and birth injuries across Indiana. We have the experience and the clinical resources needed to understand what complex hospital records show.
Contact the Powless Law Firm today at (877) 769-5377 for a free, confidential consultation. We will listen to your delivery story, help you obtain your child’s medical records, and explain your options. There is no fee unless we win your case.
The Powless Law Firm represents families across Indiana, from Indianapolis to Fort Wayne and Evansville, in cases involving birth trauma lawsuits, medical malpractice birth injury claims, and cerebral palsy lawsuits. As experienced medical malpractice attorneys in Indiana, we are here to listen to your story and help you find the way forward.